What are the potential effects of Anadrol on the liver
Oxymetholone, commonly known as Anadrol, is a synthetic androgenic-anabolic steroid heavily scrutinized for its impact on metabolic health and hepatic function. Toxicological models demonstrate that its administration induces specific markers of oxidative stress, notably elevating malondialdehyde and depleting endogenous glutathione. Evaluating this relationship requires examining structural cellular changes rather than relying solely on symptomatic indicators of liver damage.
01 — The mechanistic basis of hepatic stress
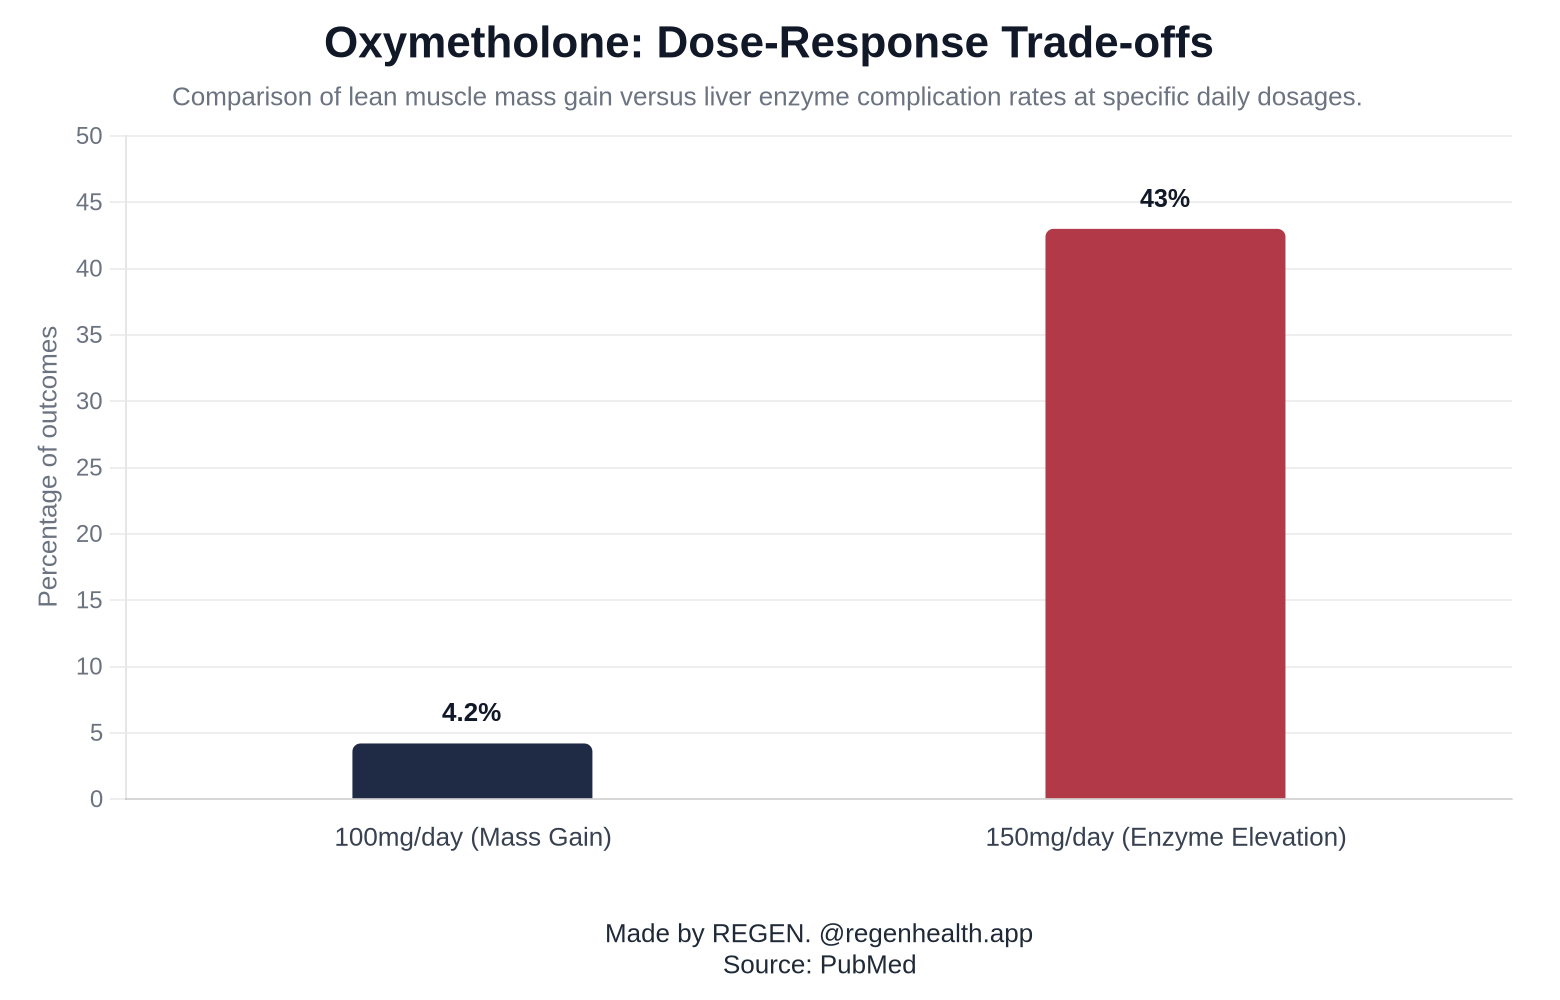
Oxymetholone exerts well-documented stress on hepatic tissues through mechanisms that extend beyond transient functional fluctuations. In rodent models, oral administration of 10 mg/kg oxymetholone significantly increased serum ALT and AST levels and elevated malondialdehyde while decreasing GSH. This disruption in the hepatic microenvironment highlights a direct pharmacological burden on cellular antioxidant defenses. The elevation of alanine aminotransferase and aspartate aminotransferase serves as a primary quantitative signal of hepatocellular permeability and structural compromise.
When hepatocytes metabolize synthetic androgens, the resulting oxidative burden often outpaces the organ's innate clearance capacity. The parallel depletion of glutathione indicates that the cellular defenses are actively neutralized by the compound. Similar considerations regarding systemic tissue responses and cellular preservation are evaluated in research involving compounds like BPC-157, though the specific mechanisms of action differ entirely. For oxymetholone, the primary consequence of this metabolic pathway is sustained hepatocellular stress.
02 — Depletion of antioxidant capacity
The relationship between oxymetholone exposure and oxidative damage is explicitly mapped through the measurement of endogenous antioxidants. Research indicates that oral administration of 5 mg/kg/day oxymetholone for 30 days in mice caused a significant decrease in total antioxidant capacity and catalase activity and increased malondialdehyde levels. Malondialdehyde acts as a principal biomarker for lipid peroxidation, meaning that the lipid bilayers of hepatic cells undergo direct oxidative degradation in the presence of the steroid.
The concurrent suppression of catalase activity further reduces the capacity of the hepatic tissue to neutralize reactive oxygen species. Without these crucial enzymatic defenses, the liver is subjected to a state of unmitigated oxidative stress. This biochemical environment accelerates the degradation of cellular membranes and disrupts normal metabolic processing, laying the groundwork for more severe and permanent structural anomalies if the exposure remains continuous.
03 — Structural pathology and cellular foci
Beyond acute oxidative stress and enzyme elevation, prolonged exposure to oxymetholone is associated with cumulative structural changes in liver tissue. Experimental protocols have demonstrated that administration of 0.2% oxymetholone for 4 weeks followed by 0.1% for 35 weeks significantly increased the number and area of GST-P positive liver cell foci in rats initiated with N-diethylnitrosamine. Placental glutathione S-transferase (GST-P) positive foci are established preneoplastic cellular lesions in toxicological research.
The expansion of these foci indicates that continuous pharmacological exposure facilitates permanent structural pathology rather than temporary functional suppression. When GST-P positive areas increase in size and number, the hepatic architecture undergoes modifications that do not simply reverse upon cessation of the compound. This highlights the critical distinction between short-term enzymatic spikes and the induction of long-term cellular restructuring associated with continuous androgen exposure.
04 — Toxicological and carcinogenesis evaluations
Federal and institutional frameworks have formally assessed the long-term biological consequences of oxymetholone exposure to establish definitive safety profiles. The National Toxicology Program conducted extensive toxicology and carcinogenesis studies of oxymetholone in F344/N rats and B6C3F1 mice to document these effects. These comprehensive evaluations were designed to identify the specific physiological outcomes resulting from controlled administration in mammalian subjects.
By utilizing these standardized models, researchers can isolate the exact variables that contribute to hepatic morbidity. The data from these models reinforce the necessity of monitoring cellular responses systematically, documenting the progression from baseline metabolic stress to overt toxicity. Such evaluations form the bedrock of understanding how synthetic androgens universally burden mammalian liver tissue.
05 — The role of glutathione in mitigating damage
Glutathione (GSH) depletion remains the central mechanistic driver of oxymetholone-induced hepatic toxicity. As previously established, oral administration of 10 mg/kg oxymetholone significantly increased serum ALT and AST levels and elevated malondialdehyde while decreasing GSH in rat models. Because GSH is the primary intracellular reducing agent, its rapid depletion leaves hepatocytes entirely vulnerable to accumulated reactive oxygen species.
Evaluating this metabolic pathway requires examining the precise ratio of reduced to oxidized glutathione over the course of chemical administration. Approaches to cellular preservation and tissue signaling in research often parallel systemic mechanisms observed in studies of peptides like GHK-Cu, which also interact heavily with foundational cellular signaling pathways. In the context of oxymetholone, the inability to maintain adequate GSH reserves directly dictates the severity of subsequent lipid peroxidation.
06 — Monitoring oxidative stress markers
Understanding the specific timelines for physiological deterioration requires shifting focus from general clinical symptoms to granular, longitudinal data. When 5 mg/kg/day oxymetholone for 30 days in mice caused a significant decrease in total antioxidant capacity and catalase activity and increased malondialdehyde levels, it established a definitive timeframe for measurable hepatic decline. These metrics indicate that significant lipid peroxidation occurs well within a standard 30-day window.
Consequently, tracking liver health during any level of exposure necessitates the pre- and mid-assessment of these specific biochemical markers. Monitoring AST and ALT provides evidence of active cellular damage, but assessing MDA and GSH levels offers a more precise indication of the underlying oxidative environment before catastrophic architectural changes manifest in the tissue.
07 — Regulatory status and clinical context
Oxymetholone was developed and FDA-approved for human use strictly as an adjunct treatment for specific forms of anemia; however, its application must be contextualized by its profound impact on hepatic function. It is classified as a Schedule III controlled substance in the United States. The compound is heavily restricted, and its prescribed use is limited to strictly indicated medical scenarios where the potential hematological benefits are deemed to outweigh the well-documented risks.
The evidence demonstrating that administration of 0.2% oxymetholone for 4 weeks followed by 0.1% for 35 weeks significantly increased the number and area of GST-P positive liver cell foci in rats initiated with N-diethylnitrosamine underscores the stringent medical oversight required. Any administration carries inherent risks of severe hepatotoxicity, necessitating continuous monitoring by qualified healthcare providers to manage the inevitable hepatic burden.
FAQ
What drug is the hardest on your liver?
Acetaminophen is frequently cited as the most common pharmaceutical cause of acute liver failure, though oral anabolic steroids like oxymetholone are specifically recognized for inducing profound, dose-dependent hepatic toxicity and oxidative damage. The specific severity depends entirely on the dosage, duration, and the individual's baseline metabolic health.
What are the potential effects of Anadrol on the liver?
Anadrol (oxymetholone) causes significant depletion of endogenous glutathione, spikes in malondialdehyde, and sharp elevations in ALT and AST enzymes. Long-term exposure in animal models has been shown to induce structural changes, including the formation of GST-P positive cellular foci.
How liver toxic is testosterone?
Injectable testosterone typically bypasses the first-pass hepatic metabolism that makes oral androgens highly toxic, resulting in a significantly lower burden on the liver. Unlike C17-alpha alkylated oral steroids like oxymetholone, standard therapeutic doses of injectable testosterone do not characteristically induce major elevations in liver enzymes.
What are the four warning signs of a damaged liver?
Clinical signs of a damaged liver include jaundice (yellowing of the skin and eyes), severe abdominal pain and swelling, chronic fatigue, and unusually dark urine. However, biochemical markers of oxidative stress, such as elevated MDA and depleted GSH, often manifest long before these physical symptoms appear.